“Can it come back?” is one of the questions I’m asked most often before hiatus hernia surgery. The honest answer is yes. Recurrence is the main long-term weakness of this operation. But it doesn’t happen at random. When you look at why repairs fail, the same few reasons come up again and again. Understanding them is how we prevent them, and they shape every step of how I do the operation.
First, what is a hiatus hernia?
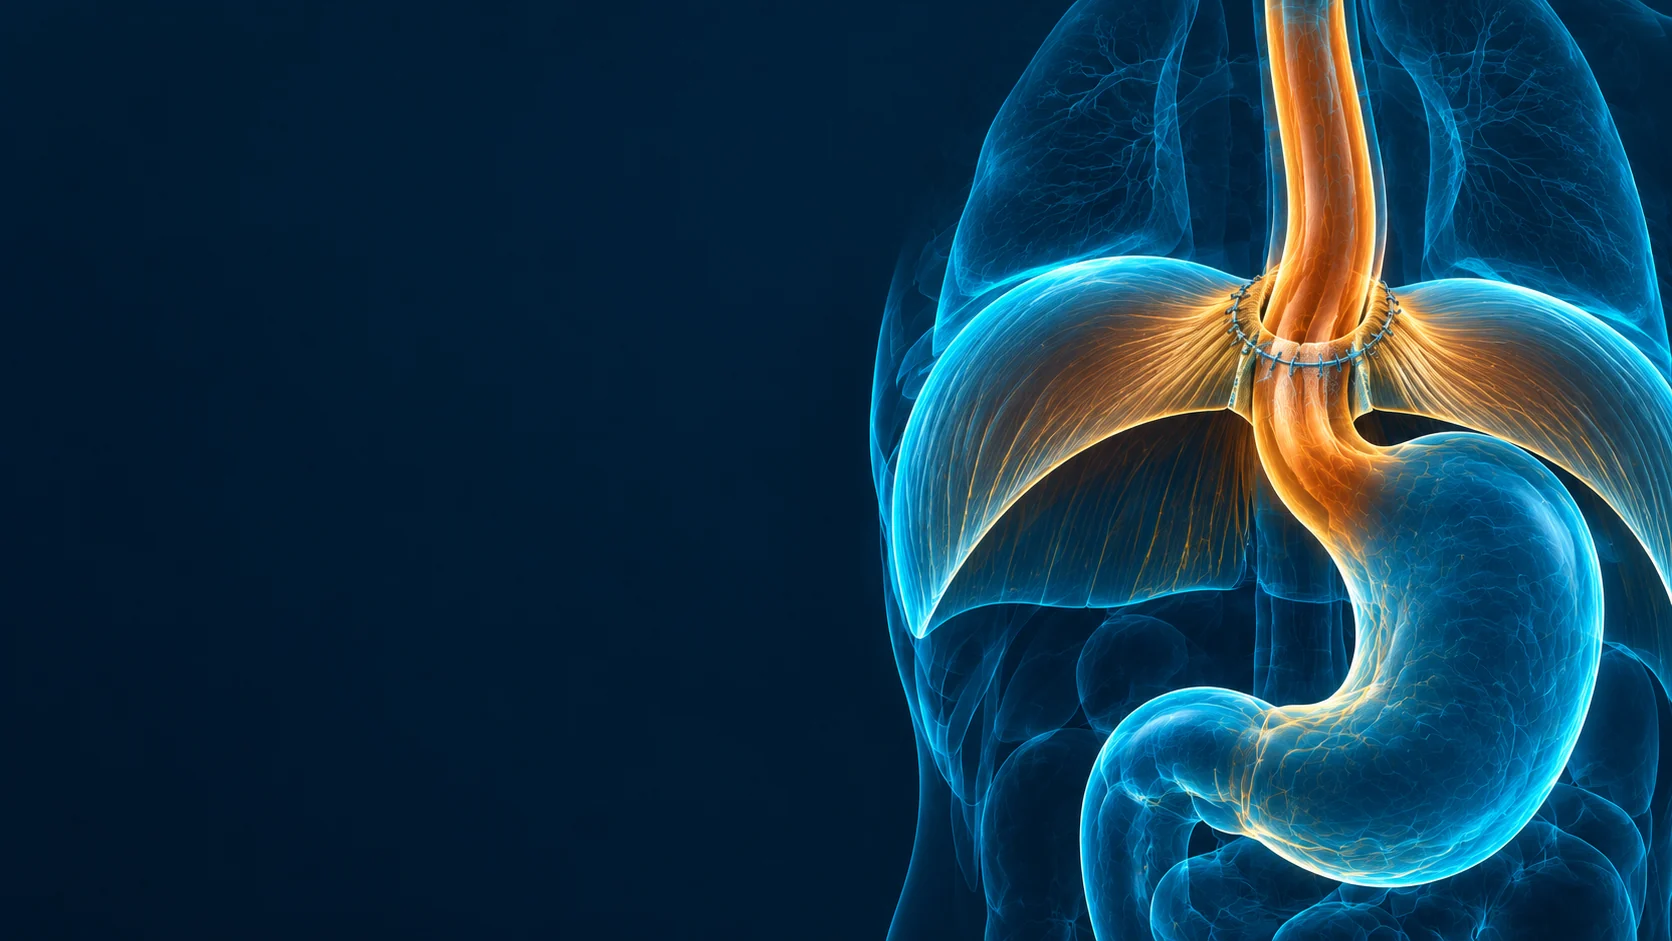
Your esophagus (food pipe) passes from the chest into the abdomen through an opening in the diaphragm called the hiatus. The diaphragm is the dome-shaped breathing muscle that separates the chest from the abdomen. The two muscular pillars on either side of this opening are called the crura. A hiatus hernia happens when the opening stretches and part of the stomach slides or pushes up into the chest. Surgery brings the stomach back down, tightens the opening, and usually rebuilds the valve that stops reflux.
How often do hiatus hernias come back?
It depends mostly on the size of the hernia, and on how closely you look. When patients with large hernias have X-rays after surgery, rather than being asked only about symptoms, small recurrences turn out to be common. In one well-known study, 42% of large hernias showed some recurrence on testing.1 In a five-year trial, more than half of patients had some recurrence on X-ray.2 Many of these are small and cause no symptoms, and most never need another operation. But these numbers are the reason I take prevention so seriously.
Why this repair is so hard to hold
The hiatus is a tough place for a repair. The diaphragm moves with every breath, about 20,000 times a day, and with every cough, sneeze, laugh and strain. On top of that, the pressure in your abdomen is higher than the pressure in your chest, so the stomach is constantly being pushed upward. A repair here is tested every minute, for the rest of your life.
The risk factors for recurrence
1. Extra body weight
Weight carried around the abdomen raises the pressure inside the abdomen and pushes the stomach up against the repair. In one study of reflux operations, the repair failed in 31% of patients with obesity, compared with 4.5% of patients at a normal weight.3 That is why weight is part of my conversation with every patient before surgery.
The sleeve-Nissen. For patients with a body mass index (BMI) of 35 or more who also have a hiatus hernia or reflux, I now offer a sleeve-Nissen. In a single operation, I:
- repair the hiatus hernia,
- perform a sleeve gastrectomy, making the stomach smaller so you lose a significant amount of weight, and
- wrap the top of the stomach around the esophagus (a Nissen wrap) to control reflux.
The wrap matters because a sleeve on its own can make reflux worse. My reasoning is simple: if extra weight helps push a hernia back up, then losing that weight should take pressure off the repair. A 2024 review of these combined operations found that only about 5% of patients had reflux afterwards, with an average of about 68% of excess weight lost.4 This is a newer operation and the long-term research is still growing, so I discuss it carefully with each patient. A gastric bypass is a well-established alternative for people with obesity and reflux, and I go over both options with you. You can read more on the weight-loss surgery page.
2. A repair stitched under tension
To close the hiatus, the two crura are stitched together. If they have to be pulled together forcefully, the stitches are under strain. Over months and years they can tear through the muscle, the way a wire cuts through cheese. A repair that is free of tension is one of the basic rules of a durable operation.5 Measurements taken during surgery show that tension at the hiatus increases with the size of the hernia.6
When the crura won’t come together comfortably, I can make a relaxing incision: a small, controlled cut in the diaphragm beside the opening. This lets the muscle come together without strain, and the small gap it leaves is covered with mesh. In the first published series, none of the repairs done with a relaxing incision had come back at about one year of follow-up.7
3. An esophagus that is too short
For the repair to stay put, a healthy length of esophagus, about 2.5–3 cm (1 inch), needs to sit comfortably below the diaphragm without being pulled down.5,8 In a long-standing hernia, years of reflux and inflammation can make the esophagus shorter. If a short esophagus is forced down into the abdomen, it acts like a stretched spring and slowly pulls the stomach back up into the chest. This is one of the most important causes of recurrence, and one of the most often overlooked.8
4. Weak, “battered” diaphragm muscle
With a large or long-standing hernia, the crura are often thin, frayed and stretched out. I describe them as “battered.” Stitches simply don’t hold as well in weak muscle. The bigger and older the hernia, the more likely this is, which is one reason large hernias come back more often.1,5
5. Not reinforcing the repair when it needs it
When the muscle is weak, the stitches can be reinforced. There are two main ways to do this:
- Pledgets. These are small felt-like pads (made of a material called PTFE) placed under the stitches. They spread the load so the stitches don’t cut through the muscle. In one series of very large hernias repaired this way, about 7% came back.9,10
- Mesh. A patch placed over the closed opening to support it. The research on mesh is mixed. Early trials found fewer recurrences with mesh,11,12 but over longer follow-up the advantage faded.2,13 Permanent plastic mesh at the hiatus can also, rarely, wear into the esophagus or stomach, which is a serious problem.14
So I don’t use permanent mesh here. I use mesh when I feel the hiatus doesn’t come together well. In that situation I reinforce the repair with Phasix, a mesh that supports the tissue while it heals and is then gradually absorbed by the body, and I consider a relaxing incision at the same time. In a study of repairs reinforced with Phasix, 8% had come back at one year, there were no mesh-related complications, and none of the patients who also had a relaxing incision or an esophageal lengthening procedure had a recurrence.15
6. Straining the repair
Anything that repeatedly raises the pressure in your abdomen puts stress on the repair. This includes a chronic cough, heavy lifting, straining on the toilet, and especially retching or vomiting in the first weeks after surgery, before the tissues have healed. One long-term study also found that younger age and previous abdominal surgery were linked to recurrence.16
How I build a repair to last
Each step of my operation is aimed at one or more of these risks:
- Free the esophagus as high as I can. I carefully release the esophagus well up into the chest so it gains length naturally. This is the most important step in avoiding a too-short esophagus.
- Check the length. I make sure a healthy segment of esophagus rests below the diaphragm without tension.
- Lengthen the esophagus if needed. On the rare occasions when it is still too short, I perform a Collis gastroplasty, which creates extra length from the top of the stomach, instead of forcing the repair.8
- Close the opening with reinforced stitches. I close the crura with permanent stitches backed by PTFE pledgets. If the hiatus doesn’t come together well, I add a Phasix mesh and consider a relaxing incision.
- Rebuild the anti-reflux valve. In most patients I use a full 360° Nissen wrap. When the esophagus doesn’t squeeze strongly on testing, I use a partial 270° Toupet wrap to lower the risk of swallowing difficulty.
- Anchor the wrap. I stitch the wrap to the diaphragm so it can’t slide back up into the chest.
- Add an anterior gastropexy for large hernias. For large and giant hernias, especially when much of the stomach has moved into the chest, I also stitch the stomach to the inside of the front of the abdominal wall. This adds security, and it has been linked to fewer recurrences in long-term follow-up.16
What you can do
- Work toward a healthy weight before and after surgery.
- Avoid heavy lifting and straining while you heal, and follow your recovery plan.
- Prevent constipation, and get a lingering cough treated.
- Tell us early about nausea or vomiting after surgery, so we can control it before it strains the repair.
- Stop smoking. It slows healing and causes coughing.
If a hernia does come back
A recurrence seen on an X-ray is not automatically a reason for another operation. If it is small and causing no symptoms, we usually just keep an eye on it. If it is causing symptoms, such as reflux, trouble swallowing, chest pain or vomiting, I consider a redo operation. Redo surgery is more complex than the first repair. The key is to find out why the first repair failed, whether that was tension, a short esophagus or weak tissue, and to fix that specific problem.
For more background, read When does a hiatus hernia actually need surgery?, my detailed approach in Dr. Irshad’s Take, and the hiatus hernia page.
Common questions
Can a hiatus hernia come back after surgery?
What makes a hiatus hernia more likely to come back?
Is mesh used in hiatus hernia repair?
What is a sleeve-Nissen?
What happens if my hiatus hernia comes back?

References
- Hashemi M, Peters JH, DeMeester TR, et al. Laparoscopic repair of large type III hiatal hernia: objective followup reveals high recurrence rate. J Am Coll Surg. 2000;190(5):553–560.
- Oelschlager BK, Pellegrini CA, Hunter JG, et al. Biologic prosthesis to prevent recurrence after laparoscopic paraesophageal hernia repair: long-term follow-up from a multicenter, prospective, randomized trial. J Am Coll Surg. 2011;213(4):461–468.
- Perez AR, Moncure AC, Rattner DW. Obesity adversely affects the outcome of antireflux operations. Surg Endosc. 2001;15(9):986–989.
- Mu SZ, Saber AA. Gastroesophageal reflux disease and weight loss after fundoplication sleeve gastrectomy: a systematic review and meta-analysis. Obes Surg. 2024;34(2):318–329.
- Kohn GP, Price RR, DeMeester SR, et al. Guidelines for the management of hiatal hernia. Surg Endosc. 2013;27(12):4409–4428.
- Bradley DD, Louie BE, Farivar AS, Wilshire CL, Baik PU, Aye RW. Assessment and reduction of diaphragmatic tension during hiatal hernia repair. Surg Endosc. 2015;29(4):796–804.
- Greene CL, DeMeester SR, Zehetner J, Worrell SG, Oh DS, Hagen JA. Diaphragmatic relaxing incisions during laparoscopic paraesophageal hernia repair. Surg Endosc. 2013;27(12):4532–4538.
- Riva P, Swanström LL. Collis gastroplasty: why, when and how? Ann Esophagus. 2018;1:12.
- Kang T, Urrego H, Gridley A, Richardson WS. Pledgeted repair of giant hiatal hernia provides excellent long-term results. J Laparoendosc Adv Surg Tech A. 2014;24(10):684–687.
- Westcott LZ, Ward MA. Techniques for closing the hiatus: mesh, pledgets and suture techniques. Ann Laparosc Endosc Surg. 2020;5:16.
- Frantzides CT, Madan AK, Carlson MA, Stavropoulos GP. A prospective, randomized trial of laparoscopic polytetrafluoroethylene (PTFE) patch repair vs simple cruroplasty for large hiatal hernia. Arch Surg. 2002;137(6):649–652.
- Granderath FA, Schweiger UM, Kamolz T, Asche KU, Pointner R. Laparoscopic Nissen fundoplication with prosthetic hiatal closure reduces postoperative intrathoracic wrap herniation: preliminary results of a prospective randomized functional and clinical study. Arch Surg. 2005;140(1):40–48.
- Watson DI, Thompson SK, Devitt PG, et al. Laparoscopic repair of very large hiatus hernia with sutures versus absorbable mesh versus nonabsorbable mesh: a randomized controlled trial. Ann Surg. 2015;261(2):282–289.
- Stadlhuber RJ, Sherif AE, Mittal SK, et al. Mesh complications after prosthetic reinforcement of hiatal closure: a 28-case series. Surg Endosc. 2009;23(6):1219–1226.
- Abdelmoaty WF, Dunst CM, Filicori F, et al. Combination of surgical technique and bioresorbable mesh reinforcement of the crural repair leads to low early hernia recurrence rates with laparoscopic paraesophageal hernia repair. J Gastrointest Surg. 2020;24(7):1477–1481.
- Poncet G, Robert M, Roman S, Boulez J. Laparoscopic repair of large hiatal hernia without prosthetic reinforcement: late results and relevance of anterior gastropexy. J Gastrointest Surg. 2010;14(12):1910–1916.